
Patient information
About supplements after bariatric surgery
Blood counts, iron, vitamin B12, vitamin D, folic acid, and possibly CRP need to be closely monitored.

Bariatric surgery is the most effective treatment for severe obesity and generally yields good long-term effects on weight and obesity-related comorbidities. The goal of the surgery is to promote weight loss through reduced calorie intake. This carries a risk of inadequate intake of essential nutrients such as vitamins and minerals. Additionally, changes to the gastrointestinal tract following surgery can lead to poorer nutrient absorption.
The importance of post-operative follow-up is evident, and it is crucial that both the bariatric surgeon and primary healthcare participate in this monitoring. Obesity-related comorbidities are common and often require treatment that is largely managed by primary healthcare. After surgery, some of these conditions may resolve or partially improve, and therefore, there is often a change in the focus of their treatment.
The stomach plays a key role in the absorption of vitamin B12 and minerals from food. Vitamin B12, iron, and zinc are all protein-bound in food, which must be broken down for mineral absorption to be possible. This occurs with the help of the enzyme pepsinogen, found in the stomach, which is most active in an acidic environment. Reduced stomach acid, shorter time in an acidic environment, and stomach acid medications (proton pump inhibitors) also lead to lower iron absorption. The absorption of vitamin B12 takes place in the lower part of the small intestine and increases with the help of the protein intrinsic factor, which is produced in the stomach. Most metabolic procedures performed today reduce stomach volume, thus leading to decreased absorption of vitamin B12 and minerals.
It is important that both women and men take supplemental iron. The proportion of those diagnosed with iron deficiency increases with the years after surgery. Before surgery, the proportion of women and men with iron deficiency is about 10%, but it increases to 17-18% 5 years post-surgery.
The vast majority of the absorption of essential nutrients occurs in the duodenum and upper part of the small intestine. These include calcium, vitamin D, iron, zinc, as well as other minerals. Over half of those who are overweight already have a vitamin D deficiency before bariatric surgery. Vitamin D is fat-soluble, and its absorption is reduced in malabsorption. The degree of malabsorption depends on the type of bariatric surgery, but in some cases, a severe vitamin D deficiency can develop, requiring potent supplementation.
Recommendations to prevent vitamin and mineral deficiency
Following bariatric surgery, the risk of iron, vitamin B12, and vitamin D deficiency is highest. Therefore, it is important that all individuals who have undergone such surgery supplement their nutrition with iron, vitamin B12, vitamin D, and calcium. Additionally, it is considered safest to take a multivitamin/mineral supplement. The table below shows the minimum recommended doses. Vitamin B12 can also be administered intramuscularly every 3 months. Vitamins and minerals are not co-paid by Icelandic Health Insurance (SÍ), and therefore, some cost may be associated with this treatment.
Recommended daily intake of nutrients after gastric sleeve and gastric bypass surgeries:

Blood count, iron, vitamin B12, vitamin D, folic acid, and possibly CRP must be monitored closely. During the first year after surgery, several blood tests are taken at regular intervals, but if these values are good and change little throughout the year, the time between subsequent follow-ups can be extended. It is not recommended to stop taking supplements even if blood tests turn out well, as deficiency can develop over the long term. If values are not within range, monitoring must be tightened. Obesity is often accompanied by chronic inflammation in the body, and CRP values frequently decrease after surgery. These recommendations are for preventive treatment and are not sufficient if a deficiency in certain values is present. Likewise, it is expected that these recommendations will not suffice if a deficiency existed prior to surgery. In addition, special attention must be paid to subgroups such as pregnant women and patients with chronic inflammatory bowel diseases.

More articles

Diet after bariatric surgery
Here, Dagný Ólafsdóttir goes over dietary guidelines that are important to keep in mind when undergoing bariatric surgery.
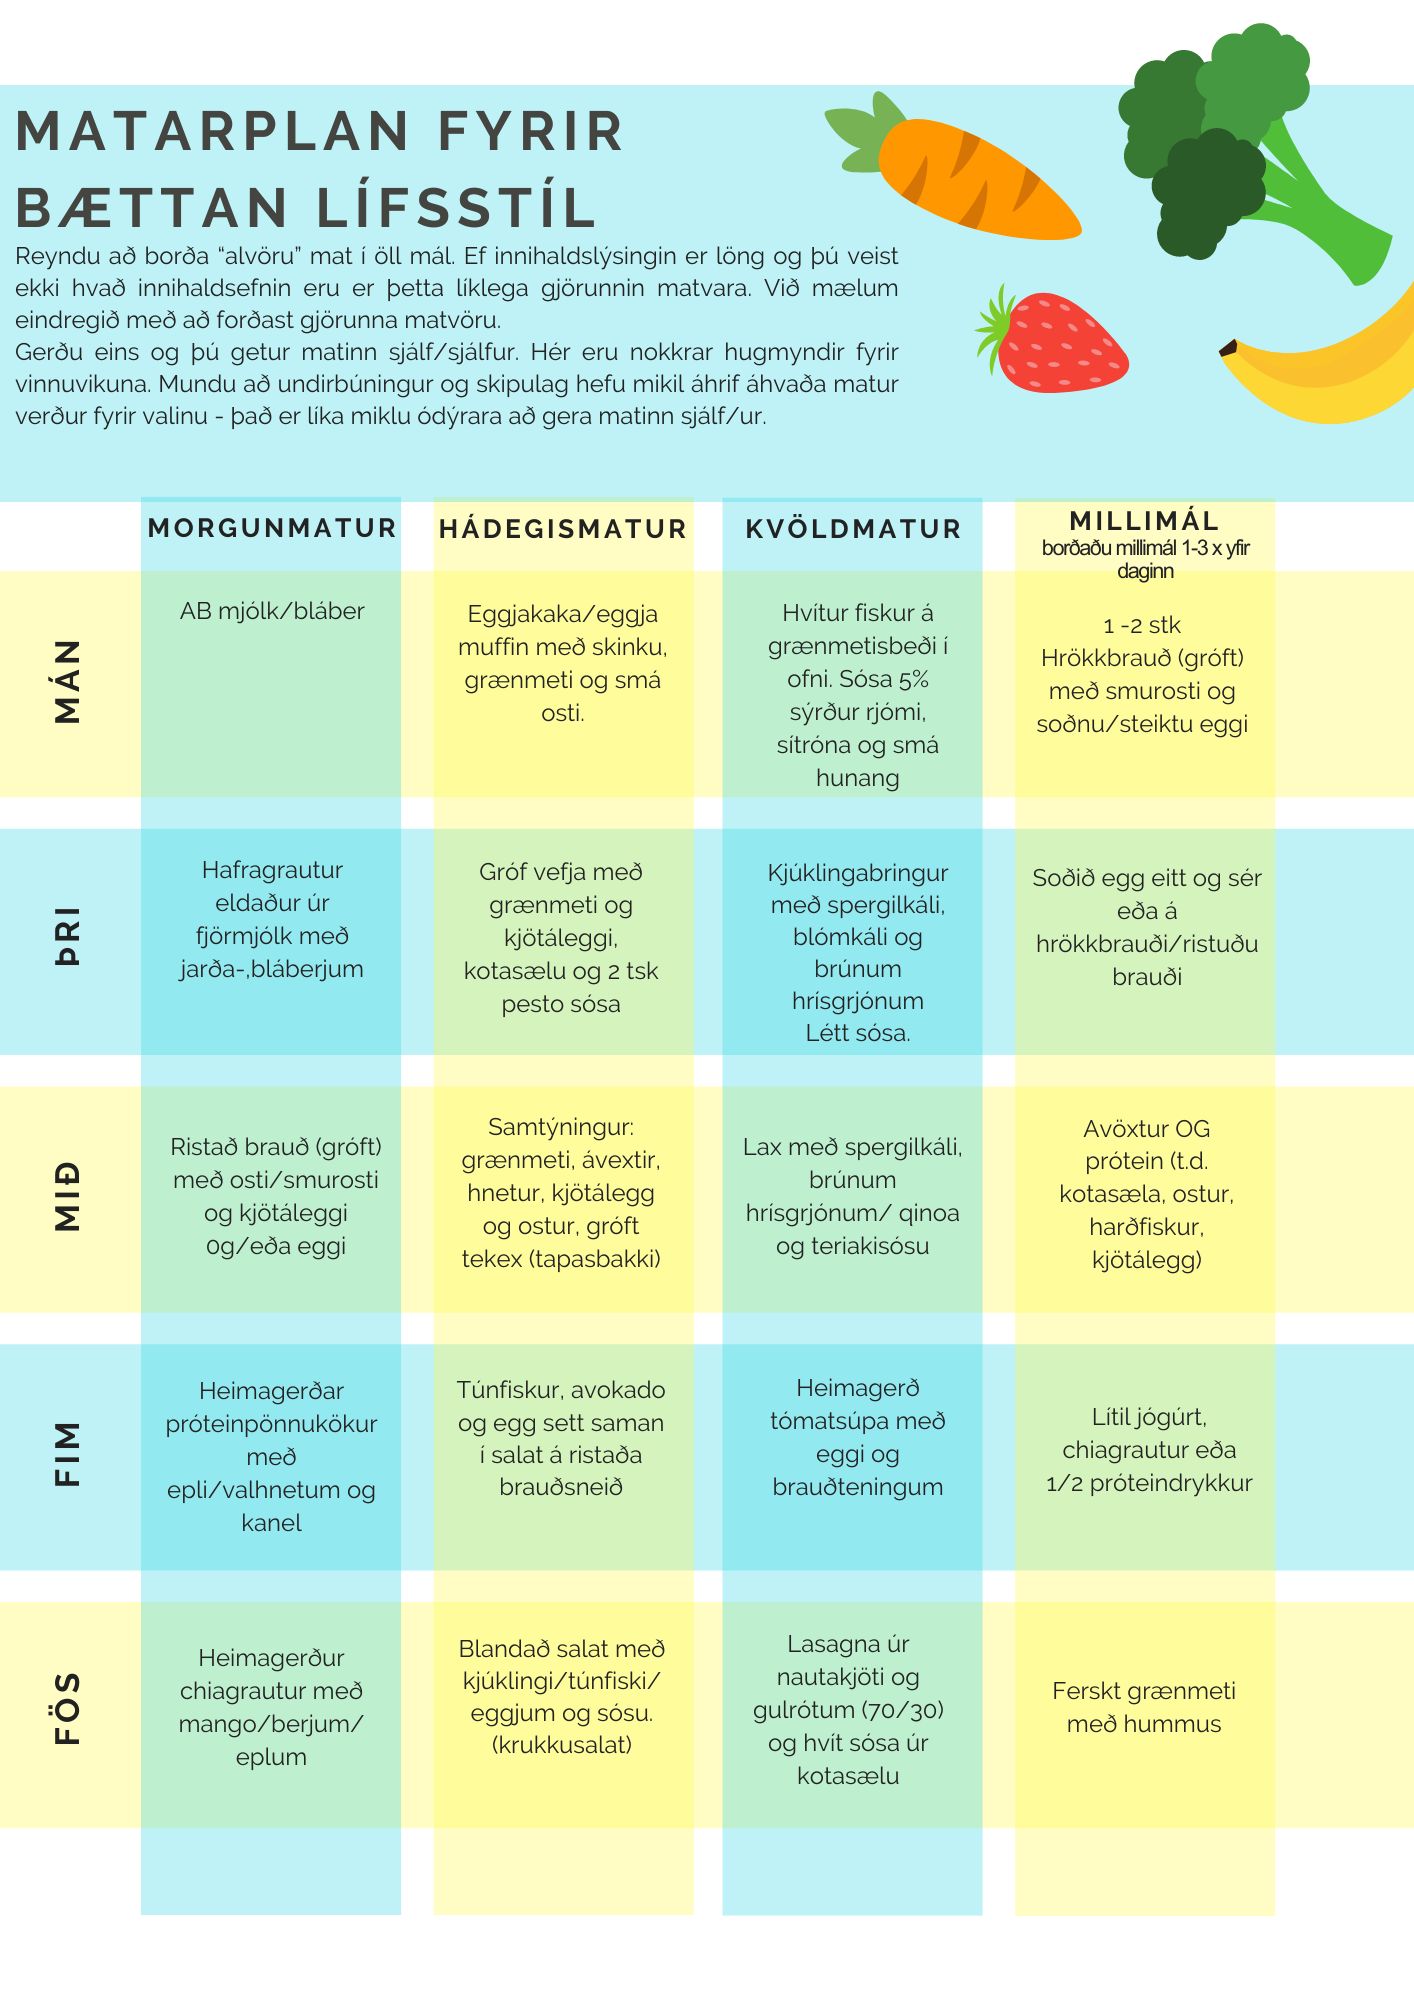
Meal ideas
What should I eat? Ideas for meals.

Pain medication after bariatric surgery
It is important to choose the right painkiller.

Constipation, what can be done?
Constipation is a very common complication after bariatric surgery.

